
LUMAKRAS® is indicated for the treatment of adult patients with KRAS G12C-mutated locally advanced or metastatic non-small cell lung cancer (NSCLC), as determined by an FDA-approved test, who have received at least one prior systemic therapy.
This indication is approved under accelerated approval based on overall response rate (ORR) and duration of response (DOR). Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s).

LUMAKRAS® (sotorasib), a first-in-class KRASG12C inhibitor, was FDA approved with accelerated approval in May 20211,2
CodeBreaK 100 was a single-arm, open-label, global, multicenter clinical trial with the Phase 2 portion evaluating
LUMAKRAS® (sotorasib) in 126 patients with locally advanced or metastatic KRAS G12C–mutated NSCLC who progressed on prior therapy. Major efficacy outcomes in patients with ≥ 1 measurable lesion (BICR according to RECIST v1.1; n=124) were objective response rate (36% [95% CI: 28–45]; CR: 2%, PR: 35%) and duration of response (median: 10.0 months [range 1.3+, 11.1]; ≥ 6 months: 58% of patients observed beyond landmark time).1,3
*Treat until disease progression or unacceptable toxicity.1

LUMAKRAS® is the #1 prescribed KRASG12C inhibitor4,†

LUMAKRAS® is supported by the longest clinical follow-up and the largest pooled safety analysis among KRASG12C inhibitors5,‡

In 2022, LUMAKRAS® won the Prix Galien USA award for Pharmaceutical Agent6,§


†Based on IQVIA LAAD data from January 1, 2023 to March 31, 2026 among patients with metastatic lung cancer and confirmed prior treatment.4
‡Trials within the pooled safety analysis included CodeBreaK 100, 101, 200, and 105.5,9
§Prix Galien USA is an independent distinction that awards pharmaceutical products introduced in the public market and achievements of research teams. To be eligible, products must have received marketing approval in the US by December 31 of the year preceding the awards, but not more than 5 years earlier than December 31 of that year, unless the award is for a new and innovative indication, which must have been added within the previous 5 years.10,11
**From June 5, 2021 to March 27, 2026. Data include new-to-brand prescriptions from specialty pharmacies. There is a deidentified patient ID associated with each Rx that allows differentiation between new patients and refills.7
††From June 5, 2021 to March 20, 2026. Data sources include specialty pharmacy data, IQVIA XPO, IQVIA LAAD, IntrinsiQ, IPM, and Ontada. Unique HCPs are first identified using individual data sources and then deduped to identify the total number of HCPs.8
BICR, blinded independent central review; CI, confidence interval; CR, complete response; HCP, healthcare professional; KRAS, Kirsten rat sarcoma viral oncogene homolog; NSCLC, non-small cell lung cancer; PR, partial response; RECIST, Response Evaluation Criteria in Solid Tumors.
NCCN
GUIDELINES®
RECOMMENDED
*NCCN makes no warranties of any kind whatsoever regarding their content, use, or application and disclaims any responsibility for their application or use in any way.12
†Does not include locally advanced.12
CNS, central nervous system; KRAS, Kirsten rat sarcoma viral oncogene homolog; NCCN, National Comprehensive Cancer Network; NSCLC, non-small cell lung cancer.
LUMAKRAS® is not a chemotherapy, immunotherapy, or TKI. It’s a highly selective* oral inhibitor designed
specifically for patients with
a KRAS G12C mutation1

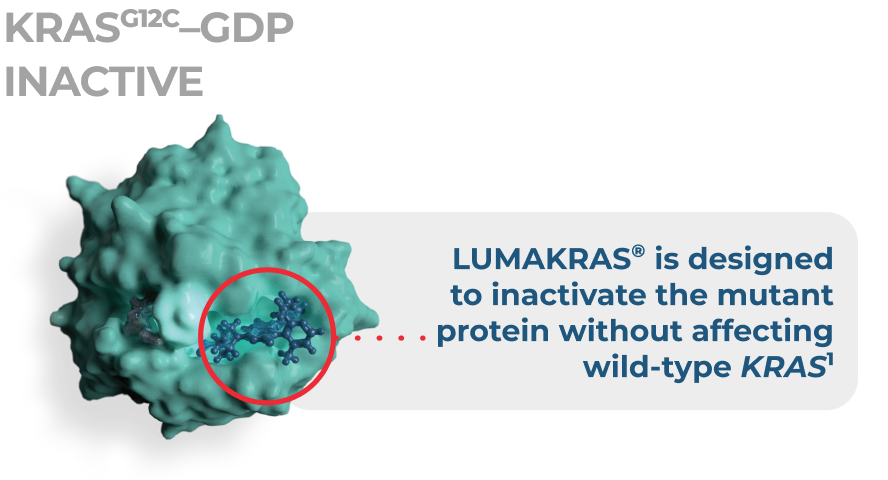
*Cysteine proteome analysis of 6,451 peptides showed sotorasib only covalently engages with Cys12 of KRASG12C. Preclinical studies in 22 cell lines and xenograft models demonstrated that sotorasib does not inhibit KRAS wild type or non-KRAS G12C lines/tumors.14
GDP, guanosine diphosphate; KRAS, Kirsten rat sarcoma viral oncogene homolog; TKI, tyrosine kinase inhibitor.
Hepatotoxicity
Interstitial Lung Disease (ILD)/Pneumonitis
Most Common Adverse Reactions
Drug Interactions
INDICATION
LUMAKRAS® is indicated for the treatment of adult patients with KRAS G12C‑mutated locally advanced or metastatic non‑small cell lung cancer (NSCLC), as determined by an FDA‑approved test, who have received at least one prior systemic therapy.
This indication is approved under accelerated approval based on overall response rate (ORR) and duration of response (DOR). Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s).
Please see full LUMAKRAS® Prescribing Information.
IMPORTANT SAFETY INFORMATION
Hepatotoxicity
References: 1. LUMAKRAS® (sotorasib) prescribing information, Amgen. 2. Food and Drug Administration. https://www.fda.gov/news-events/press-announcements/fda-approves-first-targeted-therapy-lung-cancer-mutation-previously-considered-resistant-drug. Accessed May 21, 2026. 3. Sotorasib CSR. Amgen; 2021. 4. Data on file, Amgen; [Most prescribed]. 5. Data on file, Amgen; [Trial Sites]. 6. The Galien Foundation. https://www.prnewswire.com/news-releases/the-galien-foundation-honors-2022-prix-galien-award-recipients-301662219.html. Accessed May 20, 2026. 7. Data on file, Amgen; [Unique patients]. 8. Data on file, Amgen; [Unique prescribers]. 9. Skoulidis F, et al. Oncologist. 2025;30:oyae356. 10. The Galien Foundation. https://www.galienfoundation.org/what-you-must-know. Accessed May 21, 2026. 11. The Galien Foundation. https://candidates.prix-galien-usa.com/submissions/eligibility. Accessed May 20, 2026. 12. Referenced with permission from the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for Non-Small Cell Lung Cancer. V.6.2026. ©National Comprehensive Cancer Network, Inc. 2026. All rights reserved. Accessed June 12, 2026. To view the most recent and complete version of the guideline, go online to NCCN.org. NCCN makes no warranties of any kind whatsoever regarding their content, use or application and disclaims any responsibility for their application or use in any way. 13. Referenced with permission from the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) for Central Nervous System Cancers. V.2.2026. ©National Comprehensive Cancer Network, Inc. 2026. All rights reserved. Accessed June 10, 2026. To view the most recent and complete version of the guideline, go online to NCCN.org. NCCN makes no warranties of any kind whatsoever regarding their content, use or application and disclaims any responsibility for their application or use in any way. 14. Canon J, et al. Nature. 2019;575(7781):217-223.
