Adverse reactions and safety considerations

LUMAKRAS® (sotorasib) safety and tolerability were evaluated in CodeBreaK 100 (N=204) KRAS G12C–mutated NSCLC patients1

The most common adverse reactions ≥ 20% were diarrhea, musculoskeletal pain, nausea, fatigue, hepatotoxicity, and cough in CodeBreaK 100 (N=204)1

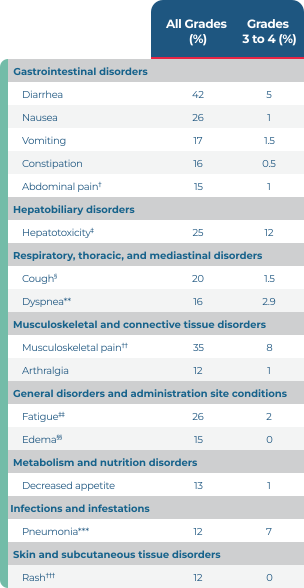
Adverse reactions (≥ 10%) of patients with KRAS G12C–mutated NSCLC who received LUMAKRAS® in CodeBreaK 100 (N=204)1,*

*Grading defined by NCI CTCAE version 5.0.1

†Abdominal pain includes abdominal pain, abdominal pain upper, and abdominal pain lower.1

‡Hepatotoxicity includes alanine aminotransferase increased, aspartate aminotransferase increased, blood bilirubin increased, drug-induced liver injury, hepatitis, hepatotoxicity, liver function test increased, and transaminases increased.1

§Cough includes cough, productive cough, and upper-airway cough syndrome.1

**Dyspnea includes dyspnea and dyspnea exertional.1

††Musculoskeletal pain includes back pain, bone pain, musculoskeletal chest pain, musculoskeletal discomfort, musculoskeletal pain, myalgia, neck pain, non-cardiac chest pain, and pain in extremity.1

‡‡Fatigue includes fatigue and asthenia.1

§§Edema includes generalized edema, localized edema, edema, edema peripheral, periorbital edema, and testicular edema.1

***Pneumonia includes pneumonia, pneumonia aspiration, pneumonia bacterial, and pneumonia staphylococcal.1

†††Rash includes dermatitis, dermatitis acneiform, rash, rash-maculopapular, and rash pustular.1

Safety considerations1

9%

discontinued LUMAKRAS® due to AR

Adverse reactions resulting in permanent discontinuation of LUMAKRAS® in ≥ 2% of patients included hepatotoxicity (4.9%)

5%

had a dose reduction due to AR

34%

had a dosage interruption due to AR

3.4%

had a Grade 5 AR

Grade 5 adverse reactions occurred in 3.4% of patients due to respiratory failure (0.8%), pneumonitis (0.4%), cardiac arrest (0.4%), cardiac failure (0.4%), gastric ulcer (0.4%), and pneumonia (0.4%)

Use of antiemetic and antidiarrheal medications in CodeBreaK 100:2
  • 26% of patients received an antiemetic

  • 32% of patients received an antidiarrheal

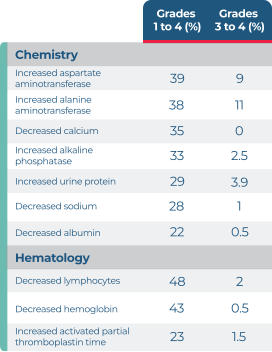
Select laboratory abnormalities (≥ 20%) that worsened from baseline (N=204)1
  • The most common laboratory abnormalities ≥ 25% were decreased lymphocytes, decreased hemoglobin, increased aspartate aminotransferase, increased alanine aminotransferase, decreased calcium, increased alkaline phosphatase, increased urine protein, and decreased sodium.

Expand to see laboratory abnormalities1

AR, adverse reaction; KRAS, Kirsten rat sarcoma viral oncogene homolog; NCI CTCAE, National Cancer Institute Common Terminology Criteria for Adverse Events; NSCLC, non-small cell lung cancer.

Monitoring

USPI monitoring and dose modification requirements for warnings and precautions1

Hepatotoxicity

Monitor liver function tests (ALT, AST, alkaline phosphate, and total bilirubin) prior to the start of LUMAKRAS®
Calendar icon

Every 3 weeks for the
first 3 months
of treatment

calender-icon-right

then once a month or as clinically indicated, with more frequent testing in patients who develop trasaminase and/or bilirubin elevation

  • Withhold, reduce the dose, or permanently discontinue LUMAKRAS® based on the severity of the adverse reaction

  • Consider administering systemic corticosteroids for the management of hepatotoxicity

ILD/pneumonitis

    • Monitor patients for new or worsening pulmonary symptoms indicative of ILD/pneumonitis (eg, dyspnea, cough, fever)

    • Immediately withhold LUMAKRAS® in patients with suspected ILD/pneumonitis and permanently discontinue LUMAKRAS® if no other potential causes of ILD/pneumonitis are identified

    For more information on adverse event monitoring and management, please see the full Prescribing Information.

    ALT, alanine transaminase; AST, aspartate transaminase; ILD, interstitial lung disease; USPI, United States Prescribing Information.

    Additional safety considerations

    Expanded Access Program

    The LUMAKRAS® global Expanded Access Program (EAP) allowed use of LUMAKRAS® for patients who had exhausted other standard-of-care treatment outside of clinical trials before receiving local regulatory approval. Two global study protocols* evaluated data from the EAP to assess the real-world safety of LUMAKRAS® 960 mg in 268 patients with locally advanced unresectable or metastatic KRAS G12C–mutated NSCLC. The primary endpoint of the protocol was safety. Study-436 (NCT04667234) and Study-442 (EudraCT #2020-005279-11) are single-arm, open-label, global, multicenter protocols under the EAP of LUMAKRAS® for the treatment of patients with KRAS G12C–mutated NSCLC.3

    The statistical reporting of safety endpoints was descriptive with no formal statistical testing performed.

    *Data cutoff for Study-436: July 5, 2024. Data cutoff for Study-442: August 11, 2022.3

    KRAS, Kirsten rat sarcoma viral oncogene homolog; NSCLC, non-small cell lung cancer.

    Baseline characteristics


    Key baseline demographics and disease characteristics of Study-436 and Study-442 of the EAP protocol (N=268)3

    • Median age
      • 66 (25–87 years)

    • ECOG performance status, %
      • ECOG PS 0, 22%

      • ECOG PS 1, 56.7%

      • ECOG PS 2, 21.3%


    • History of metastasis, %
      • 31.0% Brain

      • 11.9% Liver

    • Smoking Status, %
      • 6.3% Never

      • 16.4% Current

      • 77.2% Former

    • Sex
      • 52.2% male

    • Prior lines of advanced therapy, %
      • 34% received 1 prior line of therapy

      • 36.9% received 2 prior lines of therapy

      • 26.1% received ≥ 3 prior lines of therapy

    • Prior therapy received, %
      • 95.1% received prior platinum-based chemotherapy

      • 87.7% received prior anti–PD-[L]1 immunotherapy

      • 85.4% received prior anti–PD-[L]1 therapy +
        platinum-based chemotherapy

    EAP, Expanded Access Program; ECOG PS, Eastern Cooperative Oncology Group Performance Status; PD-1, programmed cell death protein 1; PD-L1, programmed cell death ligand 1.


    Safety analysis

    The safety profile of LUMAKRAS® in the global EAP protocol was consistent with that of CodeBreaK 1003

    The most common TRAEs of any grade (≥ 10%) were diarrhea (31.3%), nausea (12.3%), and elevated liver enzymes (ALT: 12.3%, AST: 11.9%, and ALP: 10.1%)3

    • Among the overall study population of the EAP (N=268)3

      • 6.3% discontinued LUMAKRAS® due to TRAEs

      • 27.6% had a dose reduction or interruption of LUMAKRAS® due to TRAEs

    Patients with ECOG PS 2 experienced similar rates of > Grade 3 TRAEs compared to patients with ECOG PS 0–13

    One patient (0.4%) developed treatment-related pneumonitis but subsequently died due to disease progression3

    It has been estimated that ~ 30%–40% of patients with NSCLC have 
a score of ECOG PS 23

    ALP, alkaline phosphatase; ALT, alanine transaminase; AST, aspartate transaminase; EAP, Expanded Access Program; ECOG PS, Eastern Cooperative Oncology Group performance status; NSCLC, non-small cell lung cancer; TRAE, treatment-related adverse event.

    Pooled safety analysis
    The LUMAKRAS® pooled safety analysis, across 549 patients with KRAS G12C–mutated NSCLC, is the largest safety analysis of any KRASG12C inhibitor4

    LUMAKRAS® demonstrated consistent safety across multiple clinical trials, including CodeBreaK 100, 101, 200, and 1054

    • The pooled safety population reflects exposure to LUMAKRAS® as a single agent at 960 mg orally once daily until disease progression or unacceptable toxicity in 549 patients with NSCLC with the KRAS G12C mutation.

    The only once-daily oral KRAS G12C therapy. Treat until disease progression or unacceptable toxicity1

    Hepatotoxicity1,*

    In the pooled safety analysis, regardless of time from prior immunotherapy, 94% of hepatotoxicity treatment-emergent adverse events (TEAEs) improved or resolved with dosage modification of LUMAKRAS®, with or without corticosteroid treatment.

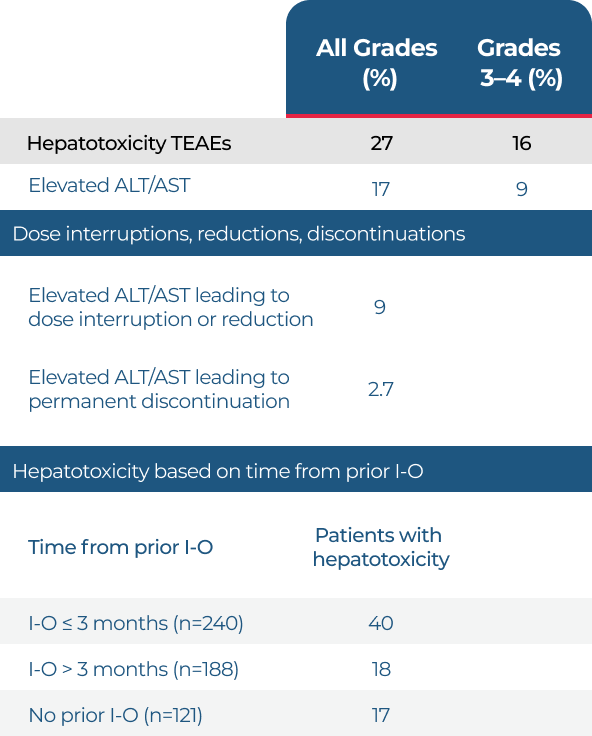
    • LUMAKRAS® can cause hepatotoxicity and increased ALT or AST, which may lead to drug-induced liver injury and hepatitis

      • Drug-induced liver injury occurred in 1.6% (all grades) including 1.3% (Grade ≥ 3)
    • Median time to first onset of increased ALT/AST was 6.3 weeks (range: 0.4–42)

    Hepatotoxicity TEAEs in the pooled safety population (n=549)1,4


      • Among patients with hepatotoxicity who required dosage modifications, 64% required treatment with corticosteroids1

      ILD/pneumonitis1

      ILD/pneumonitis TEAEs occurred in 2.2% of patients who received single agent LUMAKRAS® 960 mg

      • 1.1% were Grade ≥ 3 and 1 case was fatal

      • The median time to first onset for ILD/pneumonitis was 8.6 weeks (range: 2.1–36.7 weeks)

      • LUMAKRAS® was permanently discontinued due to ILD/pneumonitis in 1.3% of LUMAKRAS®-treated patients

      Gastrointestinal4

      Gastrointestinal treatment-related adverse events (TRAEs) were generally managed with dose interruptions and supportive care, with low rates of discontinuation associated with these reactions†,‡,§,**

      Percentage of patients experiencing Grade ≥ 1 diarrhea TRAEs (N=549)
      • Dose interruption and dose reduction of LUMAKRAS® resulted in resolution of > 90% of diarrhea TRAEs; median time to resolution was 18 days and 22 days, respectively.


      Percentage of patients experiencing Grade ≥ 1 nausea or vomiting TRAEs (N=549)

      *Hepatotoxicity includes alanine aminotransferase increased, aspartate aminotransferase increased, blood bilirubin increased, drug-induced liver injury, hepatitis, hepatotoxicity, liver function test increased, and transaminases increased.1

      †35.7% had a dose interruption due to diarrhea TRAEs; 16.4% had a dose reduction due to diarrhea TRAEs; 1.8% discontinued due to diarrhea TRAEs.4

      ‡37.5% of patients received anti-emetics for nausea; 44.1% received them for vomiting.4

      §20% of patients’ nausea led to dose interruption, 1.3% led to dose reduction, and no patients discontinued due to nausea.4

      **17.6% of patients’ vomiting led to dose interruption, 2.9% led to dose reduction, and 2.9% led to discontinuation.4

      ALT, alanine transaminase; AST, aspartate transaminase; I-O, immuno-oncology; ILD, interstitial lung disease; KRAS, Kirsten rat sarcoma viral oncogene homolog; NSCLC, non-small cell lung cancer; USPI, United States Prescribing Information.

      IMPORTANT SAFETY INFORMATION

      Hepatotoxicity

      • LUMAKRAS® can cause hepatotoxicity and increased ALT or AST which may lead to drug-induced liver injury and hepatitis.
      • In the pooled safety population of NSCLC patients who received single agent LUMAKRAS® 960 mg hepatotoxicity occurred in 27% of patients, of which 16% were Grade ≥ 3. Among patients with hepatotoxicity who required dosage modifications, 64% required treatment with corticosteroids.
      • In this pooled safety population of NSCLC patients who received single agent LUMAKRAS® 960 mg, 17% of patients who received LUMAKRAS® had increased alanine aminotransferase (ALT)/increased aspartate aminotransferase (AST); of which 9% were Grade ≥ 3. The median time to first onset of increased ALT/AST was 6.3 weeks (range: 0.4 to 42). Increased ALT/AST leading to dose interruption or reduction occurred in 9% of patients treated with LUMAKRAS®. LUMAKRAS® was permanently discontinued due to increased ALT/AST in 2.7% of patients. Drug-induced liver injury occurred in 1.6% (all grades) including 1.3% (Grade ≥ 3).
      • In this pooled safety population of NSCLC patients who received single agent LUMAKRAS® 960 mg, a total of 40% patients with recent (≤ 3 months) immunotherapy prior to starting LUMAKRAS® had an event of hepatotoxicity. An event of hepatotoxicity was observed in 18% of patients who started LUMAKRAS® more than 3 months after last dose of immunotherapy and in 17% of those who never received immunotherapy. Regardless of time from prior immunotherapy, 94% of hepatotoxicity events improved or resolved with dosage modification of LUMAKRAS®, with or without corticosteroid treatment.
      • Monitor liver function tests (ALT, AST, alkaline phosphatase, and total bilirubin) prior to the start of LUMAKRAS®, every 3 weeks for the first 3 months of treatment, then once a month or as clinically indicated, with more frequent testing in patients who develop transaminase and/or bilirubin elevations. Withhold, reduce the dose or permanently discontinue LUMAKRAS® based on severity of the adverse reaction. Consider administering systemic corticosteroids for the management of hepatotoxicity.

      Interstitial Lung Disease (ILD)/Pneumonitis

      • LUMAKRAS® can cause ILD/pneumonitis that can be fatal.
      • In the pooled safety population of NSCLC patients who received single agent LUMAKRAS® 960 mg ILD/pneumonitis occurred in 2.2% of patients, of which 1.1% were Grade ≥ 3, and 1 case was fatal. The median time to first onset for ILD/pneumonitis was 8.6 weeks (range: 2.1 to 36.7 weeks). LUMAKRAS® was permanently discontinued due to ILD/pneumonitis in 1.3% of LUMAKRAS®-treated patients. Monitor patients for new or worsening pulmonary symptoms indicative of ILD/pneumonitis (e.g., dyspnea, cough, fever). Immediately withhold LUMAKRAS® in patients with suspected ILD/pneumonitis and permanently discontinue LUMAKRAS® if no other potential causes of ILD/pneumonitis are identified.

      Most Common Adverse Reactions

      • The most common adverse reactions ≥ 20% were diarrhea, musculoskeletal pain, nausea, fatigue, hepatotoxicity, and cough.

      Drug Interactions

      • Advise patients to inform their healthcare provider of all concomitant medications, including prescription medicines, over‑the‑counter drugs, vitamins, dietary and herbal products.
      • Inform patients to avoid proton pump inhibitors and H2 receptor antagonists while taking LUMAKRAS®.
      • If coadministration with an acid-reducing agent cannot be avoided, inform patients to take LUMAKRAS® 4 hours before or 10 hours after a locally acting antacid.

      INDICATION

      LUMAKRAS® is indicated for the treatment of adult patients with KRAS G12C‑mutated locally advanced or metastatic non‑small cell lung cancer (NSCLC), as determined by an FDA‑approved test, who have received at least one prior systemic therapy.

      This indication is approved under accelerated approval based on overall response rate (ORR) and duration of response (DOR). Continued approval for this indication may be contingent upon verification and description of clinical benefit in a confirmatory trial(s).

      Please see full LUMAKRAS® Prescribing Information.

      • References: 1. LUMAKRAS® (sotorasib) prescribing information, Amgen. 2. Data on file, Amgen; [Anti-Emetics, Anti-Diarrheals]. 3. Novello S, et al. JTO Clin Res Rep. 2026;7:100974. 4. Skoulidis F, et al. Oncologist. 2025;30:oyae356.